

Millions of Americans have sleep apnea, and the vast majority (about 90 percent) are undiagnosed (1). Children can have sleep apnea, too, though it is much more common in adults (2). The Insomnia and Sleep Institute of Arizona helps patients as young as two years old to address every sleep disorder, including all types of sleep apnea.
Obstructive sleep apnea (OSA) is the most common, but central sleep apnea (CSA) also occurs. There are many reasons sleep apnea goes undiagnosed or untreated, but if you have been diagnosed, or suspect you may have it, it’s important to understand the full risks of this common disorder.
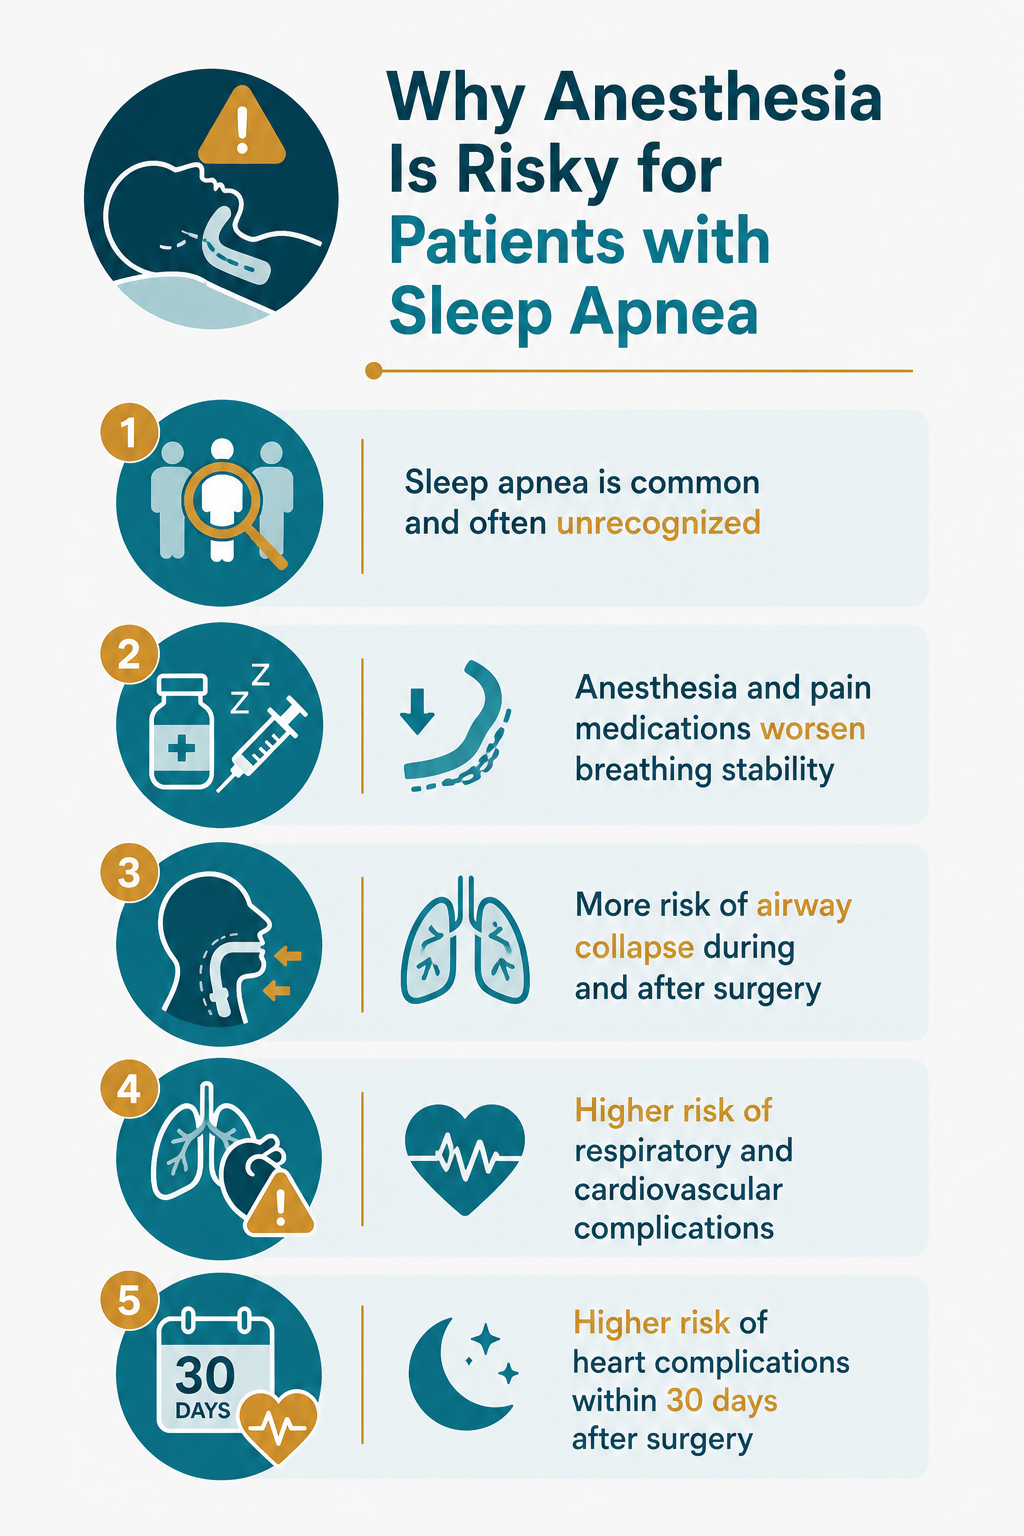
Why Anesthesia Is Risky for Patients with Sleep Apnea
Obstructive sleep apnea is common in people undergoing surgery, and many cases remain unrecognized before procedures. (3)(4)
Anesthesia, sedatives, and postoperative pain medications can worsen breathing instability because they relax the muscles that help keep the airway open and impair the body’s response to low oxygen and rising carbon dioxide levels. (4)
This makes airway collapse more likely during and after surgery, especially in patients who already have OSA. (4)(5)
Because of these effects, obstructive sleep apnea is associated with poorer perioperative outcomes, including increased risk of respiratory and cardiovascular complications. Importantly, the risk does not necessarily end after the procedure, as complications can develop in the days following surgery. (5)(4)
Research shows that patients with unrecognized severe OSA have a significantly higher risk of cardiovascular complications within 30 days after major surgery. (4) These complications are linked to prolonged periods of low oxygen levels during the first few nights after surgery, which places additional strain on the cardiovascular system. (4)
The Meeting Point of OSA and Surgery
Obstructive sleep apnea becomes more than a nighttime condition when surgery is involved. Its impact extends into the recovery period, where cardiovascular complications become a real concern.
A large prospective cohort study published in JAMA examined 1,218 patients undergoing major noncardiac surgery who were considered at risk for cardiovascular events (6). The findings showed a clear difference: 21.7% of patients with OSA experienced postoperative cardiovascular complications, compared to 14.2% of those without OSA (6).
This difference was statistically significant, but not uniform across all cases. The increased risk was primarily driven by patients with severe OSA, where the association with complications such as myocardial injury, heart failure, thromboembolism, and stroke became more pronounced (6).
The takeaway is straightforward: OSA, especially in its severe form, is not just a background condition during surgery. It is directly linked to a higher likelihood of cardiovascular events in the first 30 days after the procedure (6).
That gap, 21.7% versus 14.2%, may look like just numbers on a page, but it represents real people recovering from what they expected to be a routine procedure. These are people who said goodbye to their families in the OR and who expected to wake up sore from the procedure but ready to begin the healing process.
The American Society of Anesthesiologists echoes this concern directly, noting on their patient education platform Made for This Moment that sleep apnea “can make it more difficult to regain consciousness and take a breath after surgery”. This is a sobering reminder of how deeply this condition affects the most basic act of waking from anesthesia (7).
Unfortunately, many sleep specialists require a referral from a primary care physician, which can be a long and frustrating process. At The Insomnia and Sleep Institute, however, no referrals are needed. Home to the “Top Doc” in the area for several consecutive years,we are staffed by sleep specialists with an outcome-driven approach committed to providing correct diagnoses and effective treatment.
The Role of STOP-BANG Screening Before Surgery
Before surgery, many patients with obstructive sleep apnea remain undiagnosed. That gap matters. It can change how anesthesia is managed and how closely a patient is monitored afterward.
The STOP-BANG questionnaire was developed as a simple way to identify patients at risk. It is widely used in surgical settings because it is quick, practical, and sensitive in detecting moderate to severe OSA (8)(9). In fact, research shows it improves the ability to recognize patients who may otherwise go unnoticed (8).
Clinical guidelines support this approach. Screening tools like STOP-BANG can help flag patients early, giving care teams time to adjust perioperative planning and reduce risk (10). At the same time, screening has clear limits. STOP-BANG does not confirm obstructive sleep apnea. It is a screening tool used to identify patients at risk, and those with higher scores are recommended to undergo objective testing such as polysomnography for diagnosis (11)(12).
In practice, it serves as a first signal, not a final answer. It helps identify who may need closer evaluation, closer monitoring, and a more tailored approach to care around surgery.
Is It Safe to Have Surgery with Sleep Apnea?
Surgery is still possible for patients with obstructive sleep apnea, but the risk profile is different.
Clinical guidelines show that patients with OSA have a higher risk of perioperative complications, particularly those involving breathing and oxygen levels (13). This is partly due to how anesthesia and sedative medications affect the body. These drugs can depress respiratory drive and increase airway collapsibility, which makes breathing less stable during and after surgery (14)(15)(16).
Because of this, planning becomes essential. When a surgical team is aware of a patient’s OSA, they can adjust anesthesia choices, anticipate respiratory issues, and implement closer postoperative monitoring. Monitoring after surgery is especially important, as breathing complications can continue even after the procedure is complete.
The takeaway is simple: surgery with sleep apnea is not automatically unsafe. But without proper recognition and preparation, the risks increase. With the right precautions, those risks can be managed.
The Anesthesia Patient Safety Foundation (APSF) puts it plainly: “Careful and meticulous preparation, which begins with the preoperative assessment and extends into the postoperative period, is the key to safe anesthetic care for these patients.” In other words, the surgery itself isn’t the enemy. It’s the silence around the diagnosis. (17).
When to See a Sleep Specialist Before Elective Surgery
If you are considering elective surgery and have not seen a sleep specialist, it’s time to schedule a consultation with our sleep expert today. OSA is highly prevalent and many common symptoms are considered “normal” sleep behavior, such as snoring or waking up briefly throughout the night.
OSA can range in severity and even mild sleep apnea is associated with increased risk of post-operative cardiac events. Elective surgeries should be preceded by checking in with your local sleep specialists at The Insomnia and Sleep Institute for your safety and peace of mind. Schedule your consultation today by calling the office or filling out the online form. We see patients from Phoenix, Scottsdale, and Gilbert.
References
- Sleep Science and Sleep Disorders. (2023, September). NHLBI, NIH. https://www.nhlbi.nih.gov/science/sleep-science-and-sleep-disorders
- Pediatric Obstructive Sleep Apnea. (2022). Yale Medicine. https://www.yalemedicine.org/conditions/pediatric-obstructive-sleep-apnea
- Society of Anesthesia and Sleep Medicine: Safety of Patients with Obstructive Sleep Apnea in the Perioperative Period. (2024, October 23). Anesthesia Patient Safety Foundation. https://www.apsf.org/article/society-of-anesthesia-and-sleep-medicine-safety-of-patients-with-obstructive-sleep-apnea-in-the-perioperative-period/
- Chan, M. T. V., Wang, C. Y., Seet, E., Tam, S., Lai, H. Y., Chew, E. F. F., Wu, W. K. K., Cheng, B. C. P., Lam, C. K. M., Short, T. G., Hui, D. S. C., & Chung, F. (2019). Association of Unrecognized Obstructive Sleep Apnea With Postoperative Cardiovascular Events in Patients Undergoing Major Noncardiac Surgery. JAMA, 321(18), 1788. https://doi.org/10.1001/jama.2019.4783
- Chung, F., Memtsoudis, S. G., Ramachandran, S. K., Nagappa, M., Opperer, M., Cozowicz, C., Patrawala, S., Lam, D., Kumar, A., Joshi, G. P., Fleetham, J., Ayas, N., Collop, N., Doufas, A. G., Eikermann, M., Englesakis, M., Gali, B., Gay, P., Hernandez, A. V., & Kaw, R. (2016). Society of Anesthesia and Sleep Medicine Guidelines on Preoperative Screening and Assessment of Adult Patients With Obstructive Sleep Apnea. Anesthesia & Analgesia, 123(2), 452–473. https://doi.org/10.1213/ane.0000000000001416
- Chan, M. T. V., Wang, C. Y., Seet, E., Tam, S., Lai, H. Y., Chew, E. F. F., Wu, W. K. K., Cheng, B. C. P., Lam, C. K. M., Short, T. G., Hui, D. S. C., & Chung, F. (2019). Association of Unrecognized Obstructive Sleep Apnea With Postoperative Cardiovascular Events in Patients Undergoing Major Noncardiac Surgery. JAMA, 321(18), 1788. https://doi.org/10.1001/jama.2019.4783
- Chung, F., Yegneswaran, B., Liao, P., Chung, Sharon A., Vairavanathan, S., Islam, S., Khajehdehi, A., & Shapiro, Colin M. (2008). STOP Questionnaire. Anesthesiology, 108(5), 812–821. https://doi.org/10.1097/aln.0b013e31816d83e4
- Hwang, M., Nagappa, M., Guluzade, N., Saripella, A., Englesakis, M., & Chung, F. (2022). Validation of the STOP-Bang questionnaire as a preoperative screening tool for obstructive sleep apnea: a systematic review and meta-analysis. BMC Anesthesiology, 22(1). https://doi.org/10.1186/s12871-022-01912-1
- Practice Guidelines for the Perioperative Management of Patients with Obstructive Sleep Apnea. (2014). Anesthesiology, 120(2), 268–286. https://doi.org/10.1097/aln.0000000000000053
- Sinsopa, N., Tripakornkusol, V., Khamsai, S., & Sawanyawisuth, K. (2025). Modified STOP-Bang questionnaire for detecting obstructive sleep apnea in individuals with a body mass index below 35 kg/m 2. PeerJ, 13, e20310. The STOP-Bang Test Is Useful for Predicting the Severity of Obstructive Sleep Apnea. (2020). JMA Journal, 3(4). https://doi.org/10.31662/jmaj.2020-0002
- Faßbender, P., Herbstreit, F., Eikermann, M., Teschler, H., & Peters, J. (2016). Obstructive Sleep Apnea — a Perioperative Risk Factor. Deutsches Ärzteblatt International. https://doi.org/10.3238/arztebl.2016.0463
- Cozowicz, C., & Memtsoudis, S. G. (2021). Perioperative Management of the Patient With Obstructive Sleep Apnea: A Narrative Review. Anesthesia & Analgesia, 132(5), 1231–1243. https://doi.org/10.1213/ane.0000000000005444
- Bae, E. (2023). Preoperative risk evaluation and perioperative management of patients with obstructive sleep apnea: a narrative review. Journal of Dental Anesthesia and Pain Medicine, 23(4), 179. https://doi.org/10.17245/jdapm.2023.23.4.179
- College, W., & Singh, M. (2023, August 23). Obstructive Sleep Apnea: Perioperative Management. OpenAnesthesia. https://www.openanesthesia.org/keywords/obstructive-sleep-apnea-perioperative-management/
- Anesthesia Safety Always an Issue with Obstructive Sleep Apnea. (2024, February 15). Anesthesia Patient Safety Foundation. https://www.apsf.org/article/anesthesia-safety-always-an-issue-with-obstructive-sleep-apnea/
Disclaimer: The information provided in this blog post is for educational and informational purposes only and is not intended as a substitute for professional medical advice, diagnosis, or treatment. Always consult with a licensed healthcare provider for recommendations specific to your individual health needs.







